What causes patchy hair loss: a UK medical guide
Patchy hair loss most commonly results from alopecia areata, an autoimmune condition in which the immune system mistakenly attacks hair follicles, causing non-scarring hair loss in distinct, often coin-shaped patches. However, several other conditions can produce a similar appearance, and distinguishing between them is essential for effective treatment. The main reasons for patchy hair loss include:
- Alopecia areata:
autoimmune attack on hair follicles, producing smooth, round patches with no scarring
- Tinea capitis:
a fungal scalp infection, more common in children, often causing scaling and sometimes scarring
- Traction alopecia:
mechanical tension from tight hairstyles, typically affecting the hairline and temples
- Trichotillomania:
a compulsive hair-pulling disorder producing irregular, broken patches
- Lupus and other systemic autoimmune diseases:
can cause both scarring and non-scarring hair loss depending on the subtype
- Scarring alopecias (e.g. lichen planopilaris):
destroy follicles permanently, making early diagnosis critical
Whether the hair loss is scarring or non-scarring fundamentally shapes the prognosis. Non-scarring types, including alopecia areata, carry a realistic chance of regrowth; scarring forms do not.
Table of Contents
What is alopecia areata and who does it affect?
Alopecia areata is a chronic autoimmune condition
in which immune cells target hair follicles, triggering inflammation that halts the hair growth cycle without permanently destroying the follicle itself. Because the follicle remains intact, regrowth is biologically possible, though far from guaranteed.
The condition can affect any hair-bearing skin, including the scalp, beard, eyebrows, and eyelashes. Patches are typically smooth, round or oval, and appear without redness or scaling, which helps distinguish them from fungal infections. In some patients, the pattern known as ophiasis develops, where hair loss follows a band-like distribution along the sides and lower back of the scalp. This subtype tends to be more resistant to treatment.
“Alopecia areata is one of the most common autoimmune conditions worldwide, yet its course remains deeply unpredictable. Some patients experience a single episode and full regrowth; others face decades of relapsing and remitting hair loss.” — Primary Care Dermatology Society
About 20% of patients
report a family history of the condition, and twin studies support a clear genetic predisposition. Alopecia areata frequently co-exists with other autoimmune and atopic conditions, including thyroid disease, vitiligo, eczema, asthma, and hay fever. Progression is unpredictable: patches may resolve spontaneously, remain stable, or expand to involve the entire scalp (alopecia totalis) or body (alopecia universalis).
Symptoms and causes: how to tell different types apart
The symptoms of patchy hair loss vary considerably depending on the underlying cause, and getting the distinction right is what determines the correct treatment pathway.
Alopecia areata
produces smooth, well-defined patches, usually without itching or pain, though some patients report a mild tingling or burning sensation before a patch appears. The skin within the patch looks entirely normal.
Tinea capitis
typically presents with scaling, redness, and sometimes broken hairs at the scalp surface. It can cause scarring if left untreated, and it is contagious, making prompt diagnosis particularly important in school-age children.
Traction alopecia
follows a predictable anatomical pattern. Traction alopecia often affects the temporal area, showing a characteristic ‘fringe sign’ where a rim of preserved hair remains at the very edge of the hairline, surrounded by loss further back.
Trichotillomania
produces irregular patches with hairs of varying lengths, because pulling is rarely uniform. The patches often lack the clean borders seen in alopecia areata, and broken hairs of different lengths are a consistent feature.
- Smooth patch with normal skin surface: suggests alopecia areata
- Scaling, redness, or crusting: suggests tinea capitis or a scarring alopecia
- Irregular patch with broken hairs of uneven length: suggests trichotillomania
- Loss concentrated at the hairline or temples: suggests traction alopecia
- Scarring or follicular plugging visible on close inspection: suggests lichen planopilaris or discoid lupus
Pro Tip:
If you notice short, tapered hairs around the edge of a bald patch that are thicker at the tip than at the root, these are ‘exclamation mark hairs’, a hallmark feature of active alopecia areata that a dermatologist will look for during examination.
A thorough patient history, including hairstyling habits, family history, and any associated systemic symptoms, is as diagnostically valuable as the physical examination itself.
How is patchy hair loss diagnosed?
Diagnosis of patchy hair loss in the UK typically begins with a GP appointment. The NHS advises
seeing a GP to confirm the cause before approaching any commercial hair clinic, since the management differs substantially between conditions.
The diagnostic process usually follows this sequence:
- Clinical history:
duration of loss, pattern, associated symptoms, family history, medications, and hairstyling practices
- Scalp examination:
assessing patch shape, skin texture, scarring, and hair shaft characteristics
- Dermoscopy:
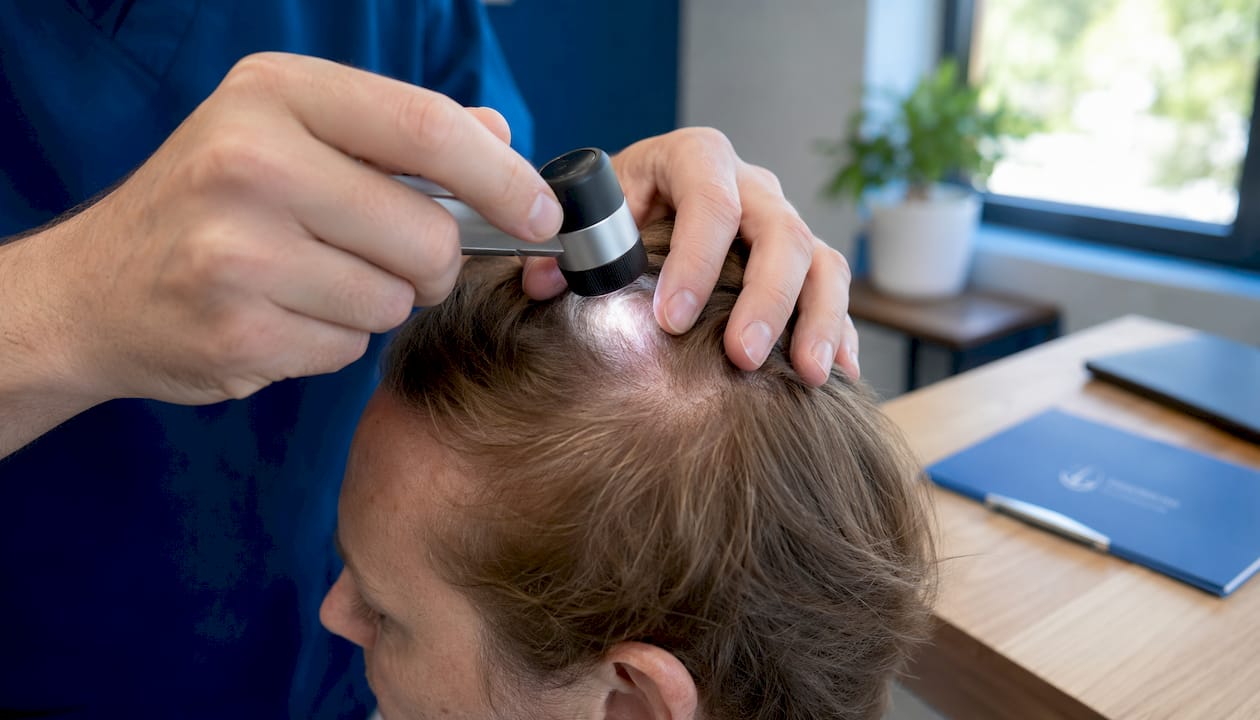
a handheld magnifying device that allows the clinician to identify diagnostic markers such as yellow dots, black dots, and exclamation mark hairs in alopecia areata, or comma-shaped hairs and scaling in tinea capitis
- Wood’s lamp examination:
useful for confirming certain fungal infections
- Scalp biopsy:
considered when the diagnosis remains uncertain, particularly to differentiate scarring from non-scarring alopecias
- Blood tests:
may include thyroid function tests, full blood count, ferritin, and autoimmune markers to exclude associated conditions or other systemic causes
Dermoscopy has significantly reduced the need for biopsy in straightforward alopecia areata cases, since the combination of yellow dots, black dots, and exclamation mark hairs is highly characteristic. Where the diagnosis is uncertain or the condition is severe, referral to dermatology is recommended.
Patchy hair loss treatments available in the UK
Treatment for patchy hair loss depends on the confirmed cause, the extent of involvement, and the patient’s age. For alopecia areata specifically, the UK healthcare system offers a structured range of options, from topical therapies to newer systemic agents.
First-line and established treatments:
- Topical corticosteroids:
applied directly to patches to suppress local immune activity; the most widely used first-line approach for limited disease
- Intralesional corticosteroid injections:
delivered into the scalp by a dermatologist, effective for small, stable patches
- Topical minoxidil:
supports hair regrowth and is often used alongside immunosuppressive treatments
- Contact immunotherapy (diphenylcyclopropenone, DPCP):
a specialist treatment that deliberately sensitises the scalp to provoke a controlled immune response, redirecting immune attack away from follicles
- Oral corticosteroids:
used short-term for rapidly progressing or extensive disease, though long-term use carries significant side effects
Newer and emerging options:
NICE recommends Ritlecitinib for patients aged 12 and above with severe alopecia areata. Ritlecitinib is a JAK inhibitor, a class of medication that blocks the inflammatory signalling pathways responsible for follicle damage. Clinical trials for JAK inhibitors have involved patients with significant scalp hair loss of several months to several years’ duration, reflecting the severity of disease these agents target. The British Association of Dermatologists supports the use of evidence-based treatments and advises patients to focus on proven therapies rather than unverified supplements or dietary changes.
Side effects vary by treatment. Topical steroids carry a risk of skin thinning with prolonged use. JAK inhibitors such as Ritlecitinib require monitoring for infections, blood count changes, and lipid levels, consistent with their systemic immunomodulatory action.
For tinea capitis, oral antifungal agents (typically griseofulvin or terbinafine) are the standard treatment, as topical antifungals do not penetrate the hair shaft adequately. Traction alopecia responds to removing the causative tension, with hair restoration options
available for cases where follicle damage is permanent. For patients exploring hair loss medication
in Glasgow, Glasgowhairtransplantclinics provides specialist guidance on both medical and surgical pathways.
Pro Tip:
Access to Ritlecitinib via the NHS may require a referral to a consultant dermatologist and confirmation that the condition meets NICE criteria for severity. Ask your GP specifically about this pathway if topical treatments have not produced adequate regrowth after several months.
Living with patchy hair loss: managing the emotional impact
The psychological burden of patchy hair loss is frequently underestimated. The unpredictable, relapsing nature of alopecia areata in particular can generate significant anxiety, and the visible nature of scalp hair loss affects self-esteem in ways that are difficult to convey to those who have not experienced it. NICE acknowledges
that management should include psychological support alongside medical treatment.
Practical steps that can help:
- Seek a formal diagnosis first:
knowing the cause removes uncertainty and gives you a treatment plan to focus on
- Talk to your GP about mental health support:
referral to a counsellor or psychologist is appropriate when hair loss is affecting daily functioning
- Connect with patient organisations:
Alopecia UK offers peer support, information, and community events specifically for people living with alopecia in the UK
- Be honest with those close to you:
explaining the autoimmune basis of the condition can help family and friends respond with informed support rather than unhelpful suggestions
- Consider camouflage options:
wigs, hairpieces, and scalp micropigmentation (SMP) are practical, non-medical options that many patients find genuinely helpful while awaiting treatment response
- Avoid unproven remedies:
the British Association of Dermatologists confirms that no dietary change or food supplement has been proven to treat alopecia areata, and pursuing these can delay effective care
The fluctuating course of the condition, with patches appearing and resolving unpredictably, makes it particularly important to maintain realistic expectations. Regrowth during a quiet phase does not guarantee the condition has resolved permanently.
Associated autoimmune conditions and UK clinical recommendations
Alopecia areata does not exist in isolation. Patients presenting with patchy hair loss should be assessed for co-existing autoimmune conditions, since alopecia areata commonly co-exists with thyroid disease (including Hashimoto’s thyroiditis and Graves’ disease), vitiligo, type 1 diabetes, pernicious anaemia, and systemic lupus erythematosus. The presence of any systemic symptoms, such as fatigue, weight change, or joint pain, warrants investigation beyond the scalp.
The genetic architecture of alopecia areata overlaps substantially with other autoimmune diseases. Genome-wide association studies have identified shared susceptibility loci between alopecia areata, rheumatoid arthritis, and coeliac disease, which helps explain why these conditions cluster in individuals and families. This immunological overlap is also why JAK inhibitors, originally developed for rheumatoid arthritis, have shown efficacy in alopecia areata.
Pro Tip:
If you have alopecia areata and develop new symptoms such as unexplained fatigue, skin changes, or joint pain, ask your GP to check thyroid function and screen for other autoimmune markers. NICE guidance supports this broader assessment in patients with confirmed alopecia areata.
NICE clinical knowledge summaries provide the primary reference framework for UK GPs managing alopecia areata, covering diagnosis, treatment escalation, and referral criteria. The British Association of Dermatologists publishes patient information leaflets and professional guidelines that dermatologists use to guide treatment decisions, particularly for moderate to severe disease. Both bodies emphasise that stress and lifestyle factors are frequently cited by patients as triggers, but the causal link remains unproven; management should focus on immunomodulatory therapies rather than lifestyle modification alone. For patients interested in understanding hair restoration approaches
used internationally alongside medical treatment, a range of options exists beyond the NHS pathway.
What is the long-term outlook for patchy hair loss?
The prognosis for patchy hair loss varies considerably depending on the underlying cause and the extent of involvement at presentation. For alopecia areata, spontaneous regrowth is possible, particularly when patches are small and the condition has been present for a short time. Patients with limited, recently developed patches have the most favourable outlook, with many experiencing full regrowth without any treatment.
However, the condition is inherently unpredictable. Some patients regrow hair fully and never experience another episode; others follow a relapsing and remitting course over many years. The ophiasis pattern, with its band-like distribution along the sides and occipital scalp, is associated with a more refractory course and lower rates of spontaneous recovery. Extensive disease, including alopecia totalis and alopecia universalis, carries a less optimistic prognosis for complete regrowth, though newer treatments like Ritlecitinib are changing outcomes for patients with severe disease.
For non-alopecia causes, the outlook depends on how quickly the underlying trigger is addressed. Traction alopecia can resolve fully if tension is removed before permanent follicle damage occurs. Tinea capitis responds well to antifungal treatment, with regrowth expected once the infection clears. Trichotillomania requires psychological intervention, and hair regrowth follows when the pulling behaviour is successfully managed. Scarring alopecias carry the least favourable prognosis for regrowth, since destroyed follicles cannot regenerate; in these cases, surgical options such as hairline transplantation
may be considered once the condition is stable.
When should you see a doctor about patchy hair loss?
See your GP promptly if you notice any of the following:
- A new bald patch appearing over days or weeks
- Patches accompanied by scaling, redness, or crusting
- Hair loss in a child, which warrants urgent assessment to rule out tinea capitis
- Associated symptoms such as fatigue, weight change, or skin changes elsewhere
- Rapid progression or loss affecting eyebrows, eyelashes, or body hair
- Any patch that appears to be scarring or shows follicular plugging
Early assessment matters because some causes, particularly tinea capitis and scarring alopecias, can cause permanent damage if left untreated. The NHS advises seeing a GP before consulting a commercial clinic, as the correct diagnosis determines the correct treatment.
Considering surgical options after medical treatment
For patients whose patchy hair loss has not responded to medical treatment, or where follicle damage is permanent, surgical restoration may be appropriate once the underlying condition is stable. Glasgowhairtransplantclinics offers Follicular Unit Extraction (FUE) hair transplants, beard and eyebrow transplants, Platelet Rich Plasma (PRP) therapy, and Scalp Micropigmentation (SMP) across Glasgow, Newcastle, and other UK locations. All surgeons are registered with the General Medical Council (GMC), and clinics hold CQC and HIS registration.
If you are ready to explore your options, Glasgowhairtransplantclinics offers a free consultation, online or face to face, to assess your suitability and discuss the most appropriate pathway for your situation. View real patient results
to understand what is achievable, or speak to the team directly about PRP treatment
as a non-surgical adjunct to medical management.
Key takeaways
Alopecia areata is the most common cause of patchy hair loss in adults, but accurate diagnosis is essential because the treatment and prognosis differ substantially between conditions.
| Point |
Details |
| Main cause is autoimmune |
Alopecia areata drives most cases of patchy hair loss through immune attack on hair follicles. |
| Family history is a risk factor |
About 20% of alopecia areata patients report a family history of the condition. |
| Dermoscopy aids diagnosis |
Exclamation mark hairs, yellow dots, and black dots help clinicians confirm alopecia areata without biopsy. |
| NICE recommends Ritlecitinib |
Ritlecitinib is approved for severe alopecia areata in patients aged 12 and above. |
| Scarring determines prognosis |
Non-scarring types carry realistic regrowth potential; scarring alopecias do not, making early diagnosis critical. |
Recommended
A new patch needs a diagnosis
Patchy hair loss can result from alopecia areata, fungal infection, repeated traction or pulling, and inflammatory conditions that cause scarring. The appearance gives clues, but it is not enough to choose treatment from an online photograph. A doctor should assess a new or unexplained patch.
Record when it appeared, whether it is expanding and any itch, tenderness, redness, scale or broken hairs. Mention changes in the beard, brows, lashes or nails as well as scalp loss.
Alopecia areata
Alopecia areata is an autoimmune condition that can cause smooth patches of loss on the scalp or other hair-bearing areas. The follicles are not usually destroyed, so regrowth is possible, but the course is unpredictable and patches may recur. It is not contagious. The British Association of Dermatologists guide
describes the condition and treatment options.
A clinician may discuss monitoring, topical treatment or injections for limited disease. More extensive disease may need specialist medicines with a careful discussion of risks and monitoring. UK funding advice does not establish eligibility or availability in Denmark; ask the treating dermatologist about the current local pathway.
Scalp infection
Tinea capitis is a fungal infection of the scalp. It can cause scaling, broken hairs and patchy loss, and an inflamed area may be tender or swollen. It is particularly common in children and can spread between people. A clinician may take samples to confirm it and prescribe treatment; shampoo alone is not a substitute for the treatment of infection in the hair follicles. See the BAD tinea capitis leaflet.
Seek prompt advice for a painful, swollen or discharging scalp or if you feel unwell. Avoid sharing combs or brushes while a possible scalp infection is being assessed, and ask the clinician about household precautions.
Pulling, tension and breakage
Styles that repeatedly pull on the scalp can cause traction alopecia. Reducing the tension early can help limit damage, while prolonged loss may become permanent. Irregular areas with broken hairs can also occur with repeated hair pulling. These appearances overlap with other causes and should be discussed without blame.
Tell the clinician about styles, extensions, adhesives and any urge to pull hair. Support for hair-pulling behaviour can be part of the plan; a cosmetic procedure alone does not address it.
Why scarring needs to be considered
Some inflammatory conditions damage and replace follicles with scar tissue. Examples include lichen planopilaris and discoid lupus affecting the scalp. The aim is to identify and treat active disease to protect remaining follicles; hair cannot reliably regrow where follicles have been destroyed.
Pain, burning, persistent redness or scaling, and areas that look smooth or shiny warrant assessment. The Primary Care Dermatology Society overview
explains the distinction between scarring and non-scarring loss. A biopsy may be needed if the diagnosis remains uncertain.
What the appointment may involve
The doctor reviews your history and examines the scalp, sometimes with magnification. Fungal samples, selected blood tests or a biopsy may be useful depending on the findings. A broad autoimmune or vitamin panel is not automatically needed for every patch.
Ask what diagnosis is most likely, what treatment is intended to achieve, which adverse effects to watch for and when to return for review. Bring a medicines list and photographs, but do not postpone an appointment while building a photo record.
Living with the change and considering restoration
Patchy loss can be upsetting even when a small area is involved. Ask about support and cosmetic camouflage if the appearance is affecting daily life. Treatment and emotional support can be considered together.
A transplant does not treat active alopecia areata, infection or ongoing scarring disease. Any later discussion of restoration needs specialist assessment of the diagnosis, stability, donor area and risk of recurrence. Contact Denmark Hair Transplant Clinics about assessment arrangements, with medical review of unexplained patches before cosmetic treatment.

About Dr Harpreet Kalra
Dr Harpreet Kalra
was born in Norway. His hair-restoration consultations consider the cause of hair loss, donor supply and the longer-term plan. UK GMC reference 7126076.
Start by establishing the cause
Contact the Denmark team about assessment. New, painful or inflamed patches should be checked by a doctor.
Request a consultation