What is traction alopecia: causes, signs, and treatment
Traction alopecia is defined as hair loss caused by chronic mechanical pulling on hair follicles, most commonly from tight hairstyles such as braids, ponytails, weaves, and extensions. The British Skin Foundation recognises it as a preventable form of hair loss, meaning the damage is avoidable when caught early. Left unaddressed, repeated tension causes progressive follicular inflammation that eventually leads to permanent scarring. Understanding the condition is the first step toward protecting your hair and scalp health.
What is traction alopecia and what causes it?
Traction alopecia is hair loss produced by sustained, repetitive tension on the hair shaft and follicle. The mechanical force does not need to be extreme to cause damage. Consistent, low-level pulling over weeks or months is enough to trigger
follicular inflammation and damage that precedes any visible hair loss.
The most common traction alopecia causes include:
- Tight ponytails and buns
pulled high or back with elastic bands
- Braids, cornrows, and dreadlocks
that place sustained tension along the hairline
- Weaves and hair extensions
that add mechanical weight to existing follicles
- Tight headbands and hair clips
worn daily over the same areas
- Rollers and hair pins
left in overnight or used repeatedly
Chemical relaxers and heat treatments compound the risk significantly. Chemical relaxers combined with traction
weaken the hair shaft structurally, making follicles far more vulnerable to mechanical stress. This means a hairstyle that might be tolerable on untreated hair can cause serious damage on chemically processed hair.
One factor that many people overlook is weight. Heavy hair and extensions exert a downward mechanical strain that is comparable to the tension from tight styling. Patients who avoid chemical treatments often assume their styling is gentle, but the physical weight alone can cause cumulative follicular damage over time.
Cultural and occupational practices also influence prevalence. Certain communities with traditions of tight braiding or weaving from childhood face a higher cumulative risk, particularly when these styles are worn continuously without rest periods.
Pro Tip:
Cumulative damage is the real danger. A single tight ponytail rarely causes lasting harm. It is the daily repetition over months and years that destroys follicles. Track how often you wear high-tension styles and build in regular rest days.
What are the symptoms of traction alopecia?
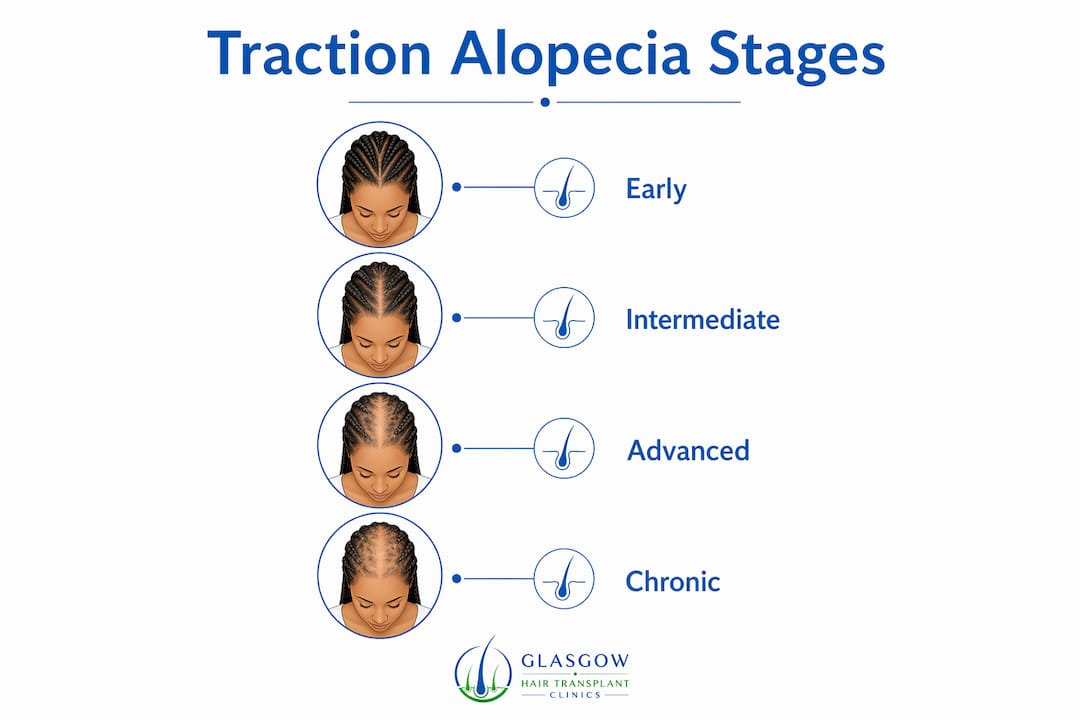
Recognising the symptoms of traction alopecia early is the single most effective way to prevent permanent hair loss. The condition progresses through distinct stages, and the window for full recovery closes once scarring begins.
Early warning signs appear before any visible hair loss:
- Scalp soreness or tenderness
along the hairline or parting after styling
- Itching and redness
at the follicle openings, known clinically as perifollicular erythema
- Flaking or scaling
of the scalp in areas under tension
- Small pimples or pustules
around hair follicles at the hairline
- Broken hairs
and short, fragile strands in high-tension zones
As the condition progresses, visible hair changes become apparent. The hairline recedes, particularly at the temples and along the front. Hair thins in the areas that bear the most tension, often forming a characteristic pattern around the forehead and ears.
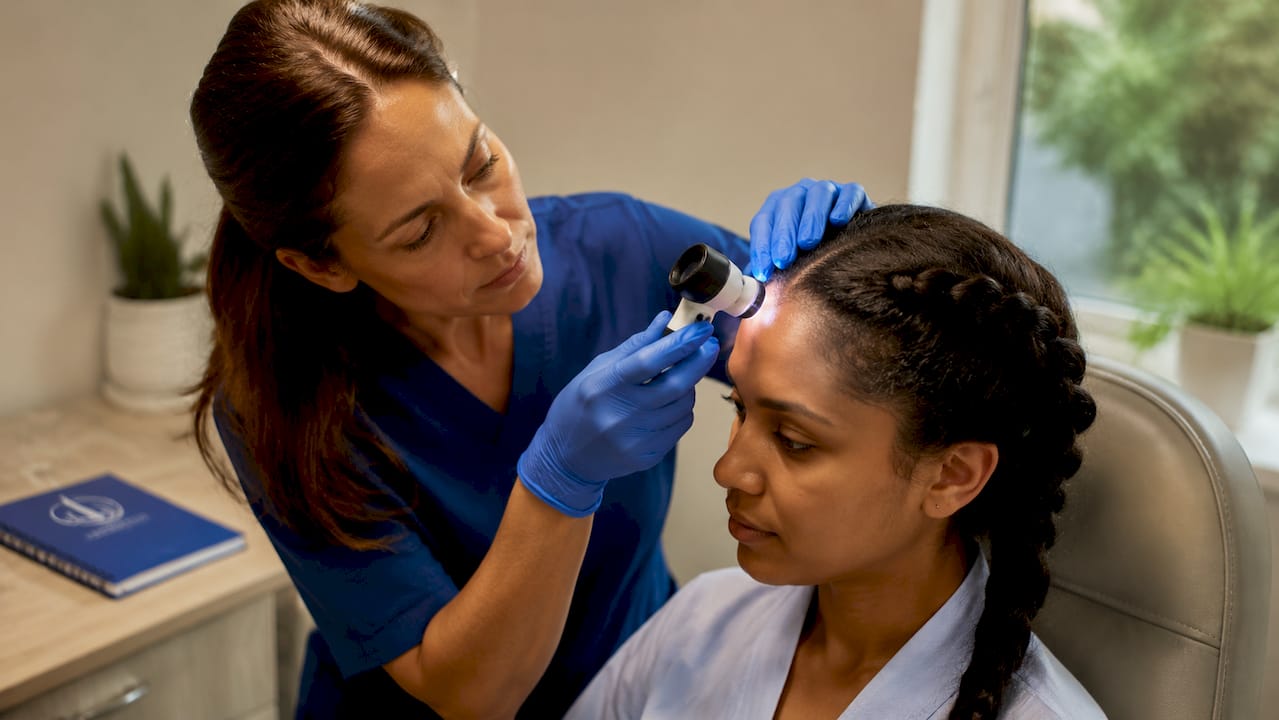
Clinicians use dermoscopy to detect changes that are invisible to the naked eye. Dermoscopy improves early diagnosis by revealing follicular miniaturisation and hair casts before significant hair loss has occurred. This makes it a valuable tool for confirming the diagnosis at a stage when treatment is still highly effective.
The “fringe sign” is a key diagnostic marker. It describes a band of short, retained hairs along the frontal hairline that indicates the follicles beneath are still viable. The fringe sign confirms follicle viability and signals that non-surgical treatment can still achieve meaningful recovery.
| Stage |
Key signs |
Follicle status |
| Early |
Soreness, itching, perifollicular erythema |
Intact, reversible |
| Intermediate |
Hairline recession, broken hairs, fringe sign present |
Partially viable |
| Advanced |
Significant thinning, scarring fibrosis |
Permanent without surgery |
How can traction alopecia be prevented effectively?
Practical prevention measures include:
- Alternating hairstyles
regularly to distribute tension across different follicle groups
- Choosing looser styles
that do not pull the hairline or temples
- Limiting extension and weave wear
to short periods with rest intervals in between
- Avoiding tight styles on chemically treated hair
, which is structurally weaker
- Using soft, fabric-covered hair ties
instead of elastic bands with metal clasps
- Sleeping on a silk or satin pillowcase
to reduce overnight friction and tension
Scalp health maintenance plays a supporting role. Keeping the scalp moisturised and avoiding harsh shampoos reduces baseline inflammation, which makes follicles more resilient to mechanical stress. Avoiding heat styling on days when you also wear tight hairstyles reduces the combined insult to the follicle.
The relationship between stylist and patient matters enormously. Hairdressers who understand traction alopecia can protect scalp health through styling choices
that reduce risk without requiring patients to abandon their preferred aesthetic entirely. Open communication about scalp sensitivity is a practical first step.
Pro Tip:
The most common mistake is ignoring scalp soreness after styling. Soreness is not normal. It is a signal that tension has exceeded what the follicles can tolerate. If your scalp aches after a new style, loosen it immediately rather than waiting for it to settle.
What treatment options are available for traction alopecia?
The first and most critical step at any stage is removing the source of tension. Stopping the damaging hairstyle immediately gives the follicles the best chance of recovery. For many patients in the early stage, this single change produces visible improvement within weeks.
Medical treatments address the inflammation and follicular damage that tension has caused:
| Treatment |
Stage |
Expected outcome |
| Corticosteroids (topical or injected) |
Early to intermediate |
Reduces inflammation, supports follicle recovery |
| Minoxidil (topical) |
Early to intermediate |
Stimulates regrowth in viable follicles |
| Platelet-rich plasma (PRP) therapy |
Early to intermediate |
Promotes follicle repair and hair density |
| Hair transplantation (FUE or FUT) |
Advanced with scarring |
Restores hair in areas of permanent loss |
Corticosteroids, minoxidil, and PRP therapy each target different aspects of follicular damage. Their effectiveness depends on the health of the remaining follicles. Once scarring fibrosis has replaced the follicular tissue, these treatments cannot restore hair in the affected area.
Platelet-rich plasma therapy is a non-surgical option that uses growth factors derived from the patient’s own blood to stimulate follicle repair. It is particularly useful in the intermediate stage, where follicles are damaged but not yet destroyed.
Hair transplantation is recommended for chronic cases where follicular damage is irreversible. Follicular Unit Extraction (FUE) is the most commonly used technique, relocating healthy follicles from a donor area to the scarred region. The procedure requires the patient to have stopped all tension-causing hairstyles before surgery and to maintain protective styling habits afterwards to protect the transplanted grafts.
Patient education is a core part of treatment at every stage. Understanding what caused the damage, and committing to changed styling habits, determines whether treatment succeeds long term.
Key takeaways
Traction alopecia is reversible when caught early, but becomes permanent once scarring fibrosis replaces the follicular tissue.
| Point |
Details |
| Early detection is critical |
Scalp soreness and redness signal damage before visible hair loss appears. |
| Cumulative tension causes the damage |
Daily repetition of tight styles over months destroys follicles gradually. |
| Prevention outperforms treatment |
Alternating styles and rest periods protect follicles more effectively than any medical therapy. |
| Treatment options vary by stage |
Corticosteroids, minoxidil, and PRP address early damage; FUE transplantation addresses permanent loss. |
| The fringe sign guides prognosis |
Its presence confirms viable follicles and a realistic chance of non-surgical recovery. |
Why early action matters more than most people realise
From working closely with patients affected by hair loss, the pattern I see most often is this: people notice the soreness, the itching, the slight recession at the temples, and they wait. They assume it will settle. They continue the same hairstyles for another year, sometimes two, before seeking advice. By that point, the window for straightforward recovery has often closed.
What strikes me most is that traction alopecia is genuinely preventable. Unlike androgenetic alopecia, which has a strong genetic component, this condition requires a specific, identifiable cause that can be removed. That makes it unusual in the world of hair loss, and it makes the delay in seeking help particularly frustrating to see.
The cultural dimension adds real complexity. For many patients, the hairstyles associated with traction alopecia carry deep personal and community significance. Telling someone to simply stop braiding their hair is not a realistic or respectful answer. The better approach is a collaborative one, working with stylists who understand scalp health, finding protective alternatives that preserve cultural identity, and monitoring the scalp regularly for early warning signs.
I also think the medical community underestimates how much patients can do for themselves once they understand the condition. Recognising that scalp soreness is a warning sign, not a normal part of styling, changes behaviour. That single piece of knowledge, applied early, prevents a great deal of permanent damage. The conversation around treating hair loss with confidence
needs to start much earlier than it currently does.
Specialist support for traction alopecia at Glasgowhairtransplantclinics
Traction alopecia responds well to early, expert assessment. Glasgowhairtransplantclinics offers both surgical and non-surgical options for patients at every stage of the condition, from PRP therapy and scalp health consultations through to Follicular Unit Extraction for advanced cases with permanent follicular loss.
All surgeons at Glasgowhairtransplantclinics are registered with the General Medical Council (GMC), and clinics hold CQC and HIS registration for your peace of mind. Whether you are noticing the first signs of hairline recession or have been living with significant thinning for years, a free consultation gives you a clear picture of your options. Book your assessment through the Glasgowhairtransplantclinics main page
and take the first step toward informed, personalised care.
FAQ
What is traction alopecia in simple terms?
Traction alopecia is hair loss caused by repeated pulling on hair follicles from tight hairstyles such as braids, ponytails, and extensions. The damage accumulates over time and becomes permanent if the tension is not removed early enough.
How long does traction alopecia last?
Early-stage traction alopecia can resolve within weeks to months once the source of tension is removed. Advanced cases involving scarring fibrosis result in permanent hair loss that requires surgical restoration.
Can traction alopecia grow back?
Hair can regrow in early and intermediate stages, particularly when the fringe sign is present, indicating that follicles remain viable. Once scarring replaces the follicular tissue, regrowth without surgical intervention is not possible.
What are the first signs of traction alopecia?
The earliest signs are scalp soreness, itching, and redness around the follicle openings after styling, known as perifollicular erythema. These symptoms appear before any visible hair loss and are the clearest signal to change styling habits immediately.
Is traction alopecia the same as other types of hair loss?
Traction alopecia differs from androgenetic alopecia and alopecia areata because it has a direct, mechanical cause that can be identified and removed. This makes it one of the most preventable forms of hair loss when recognised early.
Recommended
What causes traction alopecia?
Traction alopecia is hair loss caused by repeated pulling on the hair. Tight ponytails, buns, braids, weaves and extensions can place sustained tension on particular areas. The pattern depends on where that force is applied, rather than following one fixed pattern on every scalp.
It can affect people with any hair type. Styling practices matter, and chemical processing or heat damage may add to breakage. A hairstyle that causes pain or persistent pulling should be loosened or changed.
What signs should you look for?
Possible signs include broken hairs, thinning near the margins of the scalp, soreness, itching, redness or bumps around affected follicles. Longstanding damage may leave smoother areas where follicles have been lost. A clinician should assess these changes because several other conditions can also affect the hairline.
The “fringe sign” describes retained hairs at the edge of some affected areas. It can help a clinician recognize a pattern, but it does not prove that every follicle in the thinning area remains viable or guarantee regrowth.
Can the hair recover?
Early traction-related loss may improve when the pulling stops. Recovery takes time and depends on the extent of damage. Repeated tension over a long period can destroy follicles and leave permanent loss. The British Association of Dermatologists’ patient leaflet
explains this distinction.
Photographs taken in consistent lighting can help record changes. Avoid judging recovery from daily shedding counts or a single photograph. Ask the clinician when a review would be useful and which signs would warrant earlier reassessment.
Reducing tension is the first practical step
- Choose styles that sit loosely and do not cause persistent pulling.
- Avoid heavy extensions or accessories that increase tension on already affected areas.
- Discuss gentler styling with a hairdresser familiar with your hair type.
- Handle fragile hair carefully and avoid adding repeated heat or chemical damage.
- Seek assessment if thinning continues, the scalp is inflamed or the diagnosis is uncertain.
Changing the position of a tight hairstyle is not a substitute for removing excessive tension. Your clinician can help distinguish hair breakage from follicular loss and discuss an approach that fits your usual styling practices.
What can a clinician assess?
The history should include your hairstyles, when thinning began, symptoms, medicines, previous treatments and any other scalp concerns. Examination helps determine whether there is inflammation, scarring or a different cause of hair loss. Further investigation may be considered when the diagnosis remains unclear.
Bring photographs showing the progression and details of products or treatments already tried. The consultation-preparation guide
can help you organize that information.
Medicines and other treatments
A clinician may discuss treatment for inflammation or a trial of a hair-growth medicine in selected cases. Ask about the specific product, evidence, local prescribing status, risks and monitoring. Do not start steroid treatment or apply products to an inflamed scalp without appropriate advice.
No medicine or procedure removes the need to stop damaging traction. If PRP or another paid treatment is suggested, ask what evidence supports its use for traction alopecia specifically, what benefit is realistic and whether it would be appropriate for your stage of loss.
When might transplantation be considered?
Surgery may be discussed for selected stable areas of permanent loss after the cause has been addressed. It is not automatically suitable for every scarred or thinning hairline. The assessment needs to consider scalp health, blood supply, donor hair, expectations and the risk of further traction after treatment.
Read the donor-area guide
and discuss the proposed design before considering a graft number. New grafts also need protection from damaging styling practices.
Arranging an assessment in Denmark
Contact Denmark Hair Transplant Clinics to discuss the affected areas and the history of your hair loss. Our Copenhagen consultation address is Frederiksborggade 15, 1358 København, Denmark; appointments should be arranged before travelling.
If treatment is proposed, ask for the plan and an individual written DKK quotation. There is no need to decide on surgery before the cause and stage of the hair loss are understood.

About Dr Harpreet Kalra
Dr Harpreet Kalra
was born in Norway. His hair-restoration consultations consider the cause of hair loss, donor supply and the longer-term plan. UK GMC reference 7126076.
Discuss hairline or styling-related hair loss
The Denmark team can explain how to arrange an assessment and what information to bring.
Request a consultation